Saturday, 20 June 2020

The Clinical Applications of Southern blotting

In many areas, the use of Southern blotting has been superseded by PCR-based techniques, which are quicker, easier, and require less DNA. However, some laboratories still use Southern blotting, particularly for the investigation of 
1. Fragile X and 
2. Myotonic dystrophy. 

Both of which are associated with larger expansion sizes. First, let's have a quick think about how Southern blotting is used to investigate Fragile X syndrome.

Fragile X syndrome


Fragile X is a condition primarily affecting boys, which is characterised by an intellectual disability along with a subtle but recognisable facial appearance, which is characterised by dolichocephaly, describing a long, thin face and large ears. In addition, boys often have hyper-mobile joints. And macroorchidism can be associated.

Fragile X is an example of a triplet repeat expansion disorder. The FMR1 gene located on the X chromosome has a CGG repeat unit in the five prime untranslated region. It is usually present in less than 45 copies. Those with Fragile X syndrome have greater than 200 CGG repeats, known as a full mutation. Those with 59 to 200 repeats are known as premutation allele carriers. Premutation alleles are unstable. And when female premutations carriers pass on the gene to their offspring, there may be repeat expansion within the premutation to full mutation range. This expansion does not occur when the male premutation carriers pass on the gene.The large repeat length in the Fragile X full mutation results in methylation and subsequent inactivation of the FMR1 gene, leading to an affected male phenotype. Females with a full mutation may be more or less affected depending on the degree of X inactivation. Premutation carriers may suffer from a tremor ataxia syndrome in later life. And, in addition, female premutation carriers may suffer from premature ovarian failure.

Let's have a look at a schematic showing some possible results. The first sample is that of a normal female. Here there are two bands because, due to X inactivation, one of her X chromosomes is methylated. And the restriction enzymes used are methylation sensitive.

Skip to 0 minutes and 52 secondFragile X is an example of a triplet repeat expansion disorder. The FMR1 gene located on the X chromosome has a CGG repeat unit in the five prime untranslated region. It is usually present in less than 45 copies. Those with Fragile X syndrome have greater than 200 CGG repeats, known as a full mutation. Those with 59 to 200 repeats are known as premutation allele carriers. Premutation alleles are unstable. And when female premutations carriers pass on the gene to their offspring, there may be repeat expansion within the premutation to full mutation range. This expansion does not occur when the male premutation carriers pass on the geneThe large repeat length in the Fragile X full mutation results in methylation and subsequent inactivation of the FMR1 gene, leading to an affected male phenotype. Females with a full mutation may be more or less affected depending on the degree of X inactivation. Premutation carriers may suffer from a tremor ataxia syndrome in later life. And, in addition, female premutation carriers may suffer from premature ovarian failure. Let's have a look at a schematic showing some possible results. The first sample is that of a normal female. Here there are two bands because, due to X inactivation, one of her X chromosomes is methylated. And the restriction enzymes used are methylation sensiSkip to 2 minutes and 13 seconds
The normal male has only a single band, representing his single active X chromosome. The premutation carrier female has one normal and one premutation allele. And either of these may be subject to X inactivation and methylation, hence giving rise to four bands. The green bands represent the premutation allele. These bands can vary in intensity of their skewing of X inactivation, which can cause difficulties in interpretation. The premutation carrier male has a single band, representing his premutation allele. The full mutation alleles are large and subject to heavy methylation, resulting in poor digestion by the endonuclease and a broad smear of bands. In the full mutation female, this is present in addition to the bands from the normal allele.
However, the previous schematic represents a perfect world. This picture represents what it is more likely to look like. So we have A here, which represents the normal female. And this shows the two bands. B, which is over on the right, shows the premutation carrier female with her four bands. C, in the middle, is the premutation carrier female with skewed inactivation. So you can see the different intensity of the top band, which is the green band from the previous schema. And D shows the full mutation male, which shows that smear at the very top. Let's now think myotonic dystrophy, another triplet repeat disorder. Myotonic dystrophy is a multi-system disorder affecting both the skeletal and smooth muscle.
Skip to 3 minutes and 43 seconds
The classic feature is of myotonia, where there is sustained muscle contraction. But the condition is also associated with muscle weakness and wasting. Facially, affected individuals can have ptosis, frontal balding, and a myopathic facies, which is often associated with an open, tented mouth. In addition, myotonic dystrophy is associated with cardiac conduction defects, cataracts, and endocrine disturbance including diabetes, thyroid disorders, and hypogonads. However, myotonic dystrophy is highly variable and ranges from mildly to severely affected. The most severe form of the condition is congenital myotonic dystrophy, characterised by severe hypotonia at birth, respiratory insuffiency, and often intellectual disability. Myotonic dystrophy is caused by an expansion of a run of CTG repeats in the DMPK gene.
Skip to 4 minutes and 32 seconds
Normal DMPK alleles have up to 34 CTG repeats. Repeat lengths greater than this are unstable and may expand during meiosis such that children inheriting the gene from an affected parent are often more severely affected than their parent, a phenomenon known as anticipation. Anticipation most commonly occurs during transmission of the disease from mother to child, although it has also been rarely seen with paternal transmission. Most cases of severe congenital myotonic dystrophy occur when the neonate inherits the expanded allele from their mother. 
Testing for myotonic dystrophy is now mostly done using a triplet-primed PCR technique, which can accurately detect small to medium DMPK gene expansions. It is therefore suitable for most diagnostic and carrier testing.

Skip to 5 minutes and 21 seconds
However, triplet-primed PCR cannot currently accurately differentiate between medium and large expansions, the latter of which, if detected prenatally, increases the risk of the baby being born with congenital myotonic dystrophy. For this reason, Southern blotting is currently still being used for prenatal myotonic dystrophy testing in many laboratories though it has increasingly been superseded by newer PCR-based techniques.

Source:-https://www.futurelearn.com/courses/molecular-techniques/6/steps/765693

Friday, 19 June 2020

Southern blotting

Southern blotting may be undertaken during testing for Fragile X and other triplet repeat expansion disorders.

Southern blotting provides information about whether DNA is absent or present, the size of the DNA and how much DNA is present.
The step-by-step process is outlined below:
  1. DNA digestion. The DNA is fragmented using a restriction endonuclease enzyme.
  2. Gel electrophoresis. The DNA fragments are separated by gel electrophoresis. The fragments are separated by size with the smallest moving the furthest through the agarose gel.
  3. DNA denaturation. The DNA is denatured by immersing the gel in alkali.
  4. Blotting. The denatured DNA is transferred to a nitrocellulose membrane.
  5. Probe labelling. The membrane is exposed to a labelled probe that will seek out and hybridise to the complementary DNA fragment. After hybridisation, excess probe is washed from the membrane.
  6. Detection. If a radiolabelled probe is used, visualisation is by X-ray, or if a chromogenic detection method is used it is visualised by the development of colour on the membrane.
Image depicting the Southern blotting procedure                             Fig:- Southern blotting process
More Detail:-https://www.youtube.com/watch?v=3I9wzwj0b_A
Source:-https://www.futurelearn.com/courses/molecular-techniques/6/steps/765691

Wednesday, 17 June 2020

Multiplex Ligation Probe Amplification (MLPA)

Multiplex Ligation Probe Amplification or MLPA for short. The MLPA technique was first developed by MRC Holland. It's a technique which can be used to identify small copy number changes of DNA or RNA sequences, i.e., whether there is a deletion or duplication of a specific region of the genome. It can also be used to determine the methylation status of imprinted or promoter regions, and it can also be used to detect known points mutations, and single nucleotide polymorphisms, or SNPs. We are going to consider each of these differences in turn in this presentation. But first, we're going to think about how MLPA works. There are five basic steps that take place during the MLPA process.
The first is DNA denaturation, or separation, of the target strands of DNA. The second is hybridisation. Hybridisation of a specific MLPA probe to a specific region of the genome. The third is ligation, or both ligation and digestion, depending on what type of MLPA you are undertaking. The fourth is amplification of the probe. And the fifth is capillary electrophoresis to separate the products of the amplification process for analysis. Let's now discuss how MLPA works. MLPA probes consist of a pair of oligonucleotides which recognise adjacent target sites on the patient's DNA. The first oligonucleotide contains a region complementary to a forward primer. And the second oligonucleotide contains a region complementary to the reverse primer.


The second oligonucleotide also contains a stuffer sequence which can be of varying lengths. Denaturation of the patient DNA causes it to become single stranded, so that the oligonucleotides can hybridise to their target DNA.

In this figure, you can see two MLPA probes. One for Target A and one for Target B. And each of them consist of paired oligonucleotides. You can note that the stuffer sequence is a different length in each probe. Both oligonucleotides in this pair have correctly hybridised to their adjacent target sequence. This allows the next step of the process, ligation, to take place. If both probe target sequences have hybridised correctly and adjacently, they can be ligated together by a thermostable ligase.Skip to 0 minutes and 54 secondThe first is DNA denaturation, or separation, of the target strands of DNA. The second is hybridisation. Hybridisation of a specific MLPA probe to a specific region of the genome. The third is ligation, or both ligation and digestion, depending on what type of MLPA you are undertaking. The fourth is amplification of the probe. And the fifth is capillary electrophoresis to separate the products of the amplification process for analysis. Let's now discuss how MLPA works. MLPA probes consist of a pair of oligonucleotides which recognise adjacent target sites on the patient's DNA. The first oligonucleotide contains a region complementary to a forward primer. And the second oligonucleotide contains a region complementary to the reverse primerSkip to 1 minute and 48 seconThe second oligonucleotide also contains a stuffer sequence which can be of varying lengths. Denaturation of the patient DNA causes it to become single stranded, so that the oligonucleotides can hybridise to their target DNA. In this figure, you can see two MLPA probes. One for Target A and one for Target B. And each of them consist of paired oligonucleotides. You can note that the stuffer sequence is a different length in each probe. Both oligonucleotides in this pair have correctly hybridised to their adjacent target sequence. This allows the next step of the process, ligation, to take place. If both probe target sequences have hybridised correctly and adjacently, they can be ligated together by a thermostable ligasSkip to 2 minutes and 42 secondsSo now we have a ligated probe which has joined our paired oligonucleotides together. You will remember that the first oligonucleotide contained a region complementary to a forward primer, and the second oligonucleotide contained a region complementary to the reverse primer. Now that these oligonucleotides have been ligated together, the addition of an amplification step, using the forward and reverse primers, allows the full length of the probe to be amplified. Due to the presence of the stuffer sequence of varying length, the amplification product of each probe will be of a unique length.Skip to 3 minutes and 16 secondsThe fact that each probe will lead to the creation of amplification products of a specific and different length to the other probes means that the amplification products can now be separated by electrophoresis. And each individual amplification product will give information about a single probe within the mixture. The relative amounts of the probe amplification product will reflect the relative copy number of the target sequences.

Here's an example of what an MLPA trace would look like once the amplification probes have been separated. Here, MLPA has been undertaken for a gene called the APC gene. Each of these blue peaks represents a different probe that was targeted to a specific region of the APC gene.
You can see that the relative height of these blue lines indicate the amount of amplification product that was available for that specific probe. So if you compare the control sample to the patient sample, you can see that for Probes 11, 12, and 13, there is a half reduction in height in the case compared to the control. This indicates that there was half the amount of amplification product available, and therefore, that there was a heterozygous deletion of Exons 11 to 13 in this patient sample.
In the slide, we can see that the differences in the relative amounts of case and control DNA are reflected in the different relative peaks of the amplified probes for that region, and that can indicate if there was a deletion or a duplication in the patient DNA in that region. As well as detecting deletions and duplications, MLPA can also be used to undertake methylation-specific analysis of an imprinted region. The first three steps of MS MLPA are the same as MLPA. But a ligation and digestion step is now included.

In this figure, we see two targets. The target on the left is methylated, and the target on the right is unmethylated.The DNA is first denatured, as it was previously, splitting it into single strands. The MLPA oligo probes then hybridise to the target sequence. Simultaneous ligation and digestion of the probe DNA complex then occurs. The digestion uses a methylation-specific endonuclease. This only targets unmethylated DNA. Therefore, if the DNA is methylated, it will be protected from the endonuclease, and a normal MLPA product will be detected. This is shown on the left-hand side of the slide. If it is not methylated, the probe product will be digested, and no amplification product can be formed. Therefore, by looking for the presence, or not, of probe, we can tell whether that methylation target was methylated or not.

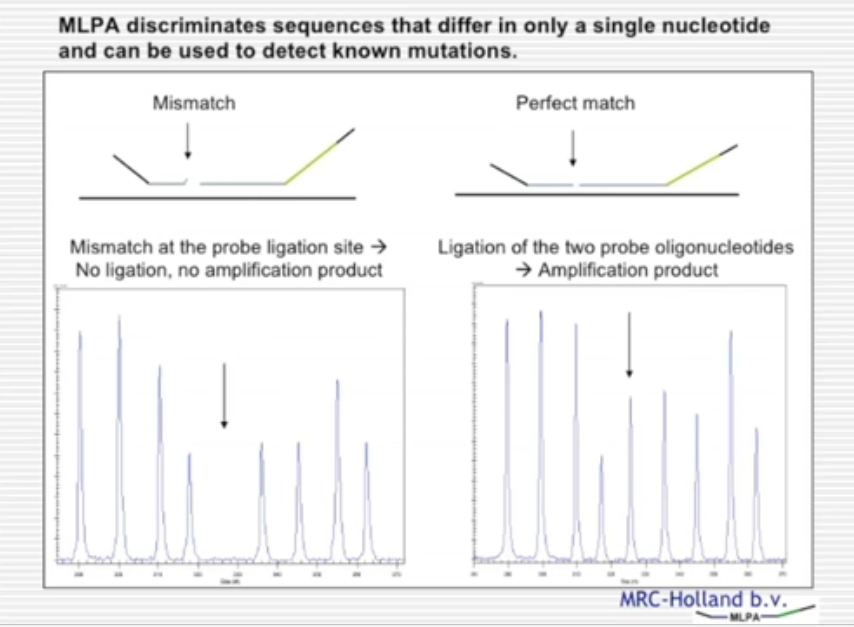
Finally, MLPA can be used for the detection of point mutations. This is based upon the principle that the oligonucleotides are exquisitely sensitive to the target DNA sequence they are designed to hybridise to. If there is a SNP or a mutation below the probe hybridisation site, then the probes will not hybridise, and no amplification product will be produced. Therefore, if there is a common mutation in a gene, a probe can be designed specific to this mutation, so the signal will only be produced when the common mutation, or SNP, is present.

This is shown in the diagram here. The diagram on the left shows normal DNA without an associated signal.
This is because the oligonucleotides have not hybridised, could not be ligated, and therefore, the probe could not be amplified. On the right; however, there's a common mutation. This allows both oligonucleotides to hybridise, ligation to occur, and an amplification product to be produced.
In summary, there are three main clinical applications for MLPA. It can be used to identify exon deletions or duplications within single genes. It can also be used to identify microdeletion syndromes, such as Di George Syndrome. Secondly, it is a powerful and rapid technique to detect methylation abnormalities. And finally, it can be used to identify common mutations.


Source:- https://www.futurelearn.com/courses/molecular-techniques/6/steps/765686

Identifying known mutations in single genes

The following PCR-based techniques are used in laboratories to investigate the common mutations.
  • ARMS-PCR (Amplification-Refractory Mutation System PCR)
    A terrible name but a simple concept! This PCR technique is a method for detecting mutations that involve a single base change or small deletion. It uses primers that are specific for certain mutations, only resulting in amplification of the PCR product if the mutation is present. It can be used to test for a single mutation, or panel of common mutations (eg in CF testing).
  • OLA (Oligonucleotide ligation assay)
    OLA can also be used to test for a group of common mutations. However in OLA it is not the presence or absence of a PCR product that is diagnostic, but the size of the product. PCR primers are used that are complementary to normal or mutant sequences, and these are each labelled with a different-sized tail. One mutation site is therefore defined by two probes. Following hybridization of the PCR primer to the complementary normal or mutant sequence there is a PCR amplification step. Then a second probe is introduced containing a 3’ fluorescent dye (FAM, TET or HEX). Ligation, using a thermostable ligase, is performed between the two probes - this will only occur when the 5’ probe matches perfectly with the target sequence. If there is a mismatch, ligation will not occur (Figure 1). The resultant ligated fluorescent probes are size-separated by electrophoresis and the presence or absence of normal and/or mutant alleles determined (Figure 2).
Figure 1. Line graph showing that the test DNA does not carry the mutation and, as a result, there is binding and subsequent ligation of the normal primer, but not the mutant primer. Figure 1: In this example, the test DNA does not carry the mutation. There is therefore binding (and subsequent ligation) of the normal primer, but not the mutant primer. 
© St George’s, University of London
Figure 2: Graph showing the result of OLA testing for the common cystic fibrosis (CF) mutations Figure 2: This image shows the result of OLA testing for the common cystic fibrosis (CF) mutations. There is a peak for each normal allele (labeled in black), and an extra peak is seen for each mutant allele (labeled in orange). Here you can see that the patient has two extra peaks, and is a compound heterozygote for the ΔF508 and 621+1G>T mutations.
© St George’s, University of London
  • PCR and restriction digest assay
PCR can also be used in conjunction with a restriction digest assay to detect common mutations, and is particularly useful for those that fall outside of normal Sanger sequencing boundaries, for example splice-site mutations.
A good example of the use of PCR and a restriction digest assay is in mutation analysis of the GJB2 gene (also known as connexin 26), a common cause of nonsyndromic sensorineural hearing loss.
Although many GJB2 mutations can be detected by GJB2 sequencing analysis, there is a known pathogenic splice site mutation (c.-23+1G>A) which is not usually included in the analysed region. However, a simple PCR and restriction digest assay can be run alongside the sequencing to detect this mutation.
A fragment spanning exon 1 and the flanking splice site is amplified by PCR. The PCR product is then digested with the HphI restriction enzyme, and the resulting fragments are size separated by gel electrophoresis. Presence of the splice site mutation alters the HphI restriction site, resulting in a larger restriction digestion product for the mutant allele than for the normal allele.
Source:-https://www.futurelearn.com/courses/molecular-techniques/6/steps/765684

Monday, 15 June 2020

The story of Fred Sanger

The story of Fred Sanger

How is it the saying goes? From little potatoes, big Nobel Prizes grow? Well, maybe not exactly that. But the story of Fred Sanger illustrates perfectly how - as so often in science, and, indeed, in life - inauspicious beginnings lead to stunning results.
Fred Sanger, the son of a Cotswolds GP and sometime missionary, started off studying physics with chemistry at Cambridge. It wasn’t the most brilliant start: he decided to give up the physics because he struggled with the maths. However, he excelled in chemistry and chose to do further studies in biochemistry. As a Quaker, he was a conscientious objector (COs) during the Second World War and was granted full exemption from military service by a tribunal. History tells us that COs were often subjected to ridicule and accused of disloyalty. Many COs contemplated going to war against their principles as their experiences of staying home were so negative. But stay, Fred Sanger did, and it was during the war years that he gained his PhD. After his first supervisor left the department, Sanger chose a new project, studying the amino acid lysine. His first paper was on the glamorous topic of the nitrogen uptake of the potato.
Proteins piqued Sanger’s interest, and joining the research group of Charles Chibnall, a protein chemist, he was encouraged to study insulin. Sanger credited Chibnall for the successful direction his career took, saying in an interview in 2007, “without him I would have continued metabolic work which would not have come to much.” Insulin seemed like a good protein to study, as in bovine form, it was available in plentiful supply from Boots (the chemist) and of course, it was medically important. However, his initial application for a grant from the Medical Research Council to study its structure was rejected, as at the time, everyone thought the pattern of amino acids in a protein was simply random.
Sanger had the last laugh, though: Working in an outbuilding he termed ‘the protein hut,’ he developed a reagent (now known as Sanger’s reagent) which identified the N-terminals of the amino groups. In doing so, he was able to show that insulin was composed of two polypeptide chains and identify the amino acids at the ends. He then used a partition chromatography method to determine the precise amino acid sequence of bovine insulin A and B in 1951 and 1952 respectively. From this discovery, he was able to conclude that by extension, every protein had a unique sequence. It was this discovery which won him the Nobel Prize for Chemistry in 1958.
The Medical Research Council, previously dismissive of his efforts, now welcomed him as the head of the protein chemistry division at their molecular biology lab in Cambridge. He started working on nucleic acids, first of all RNA. Sanger said of that time that he was lucky not to be under time pressure to produce papers as the progress was very slow. Going from sequencing proteins, a few hundred amino acids long, to much longer nucleic acids required another change in technology. But the hard work and time paid off, and by 1967, the group had sequenced the 5S ribosomal RNA structure of E. Coli. Perhaps to our modern ears, the structure of a small 120-nucleotide RNA from a bacterium most commonly heard about in food hygiene scares doesn’t sound like much, but here’s where the story really gets exciting.
Sanger, realising its importance, turned his team’s attention to sequencing DNA. Pure DNA was hard to come by but they were able to extract it from phages (viruses within bacteria). However, DNA was a dauntingly large structure, even that from the tiniest microorganism. To tackle it, Sanger knew he had to break it down. Still in the protein hut, he developed a method he called the ‘plus and minus’ method for DNA sequencing, whereby short oligonucleotides with defined 3’ termini were generated, electrophoresed and then visualised by autoradiography. This laborious process, which could sequence up to 80 nucleotides at a time, led to the first fully-sequenced DNA-based genome, that of the single-stranded bacteriophage; ϕX174.
The ‘plus and minus’ method was okay. Arduous, maybe, but nonetheless faster than its predecessors. But it had a few problems, not least of which that it could only be used for single-stranded DNA. So Sanger’s team chipped away, trying to find a better, quicker way to accurately sequence DNA. And find it they did, in 1977, in the dideoxy chain-termination method. This was based on the finding that dideoxynucleotides could inhibit chain elongation. Since dideoxynucleotides (ddGTP, ddATP, ddTTP and ddCTP) do not contain a 3’ hydroxyl group, when they were incorporated into a DNA chain in place of their corresponding deoxynucleotide (G, A, T C), no new phosphodiester bonds could be created and the growing DNA chain was terminated. So by adding a small amount of chain terminators (much less than the corresponding base) to the DNA replication mixture, Sanger’s team were able to obtain a mixture of DNA fragments of varying sizes, all with the same deoxynucleotide residues at their 3’ ends. By using corresponding terminators for each nucleotide in turn, and then electrophoresing the four different reactions in parallel, the DNA sequence could be obtained. They used this new method to sequence human mitochondrial DNA.
Of course, the dideoxy chain-termination method is what now goes by the far snappier title of Sanger sequencing. And it was this that, in 1980, secured Fred Sanger’s membership into the select group of just four individuals who have won a Nobel Prize more than once. To date, he is the only person to have won it twice for chemistry. As well as being awarded many other honours, he also supervised more than ten PhD students in his working lifetime, two of whom went on to win Nobel Prizes of their own.
Today, Sanger’s name is synonymous with DNA sequencing. It was Sanger sequencing which led to the eventual sequencing of the entire human genome in 2003. Yet throughout his career and beyond, Sanger was known for his humility. “Unlike most of my scientific colleagues,” he wrote in a 1988 article, “I was not academically brilliant.”

Source:- https://www.futurelearn.com/courses/molecular-techniques/6/steps/765681

Single Gene Abnormalities

Identifying single gene abnormalities:


1) Gene sequencing

Gene sequencing will identify point mutations and small deletions/insertions in single genes. Gene sequencing can be done by two methods:
  • Sanger sequencing involving:

i) An amplification step usually undertaken by polymerase chain reaction (PCR);
ii) A sequencing step.
  • Next generation sequencing (NGS) describing the parallel sequencing of multiple genes.

2) Dosage analysis

Multiplex Ligation-dependent Probe Amplification (MLPA) can be used to detect gene dosage abnormalities caused by exon deletions and duplications within single genes. In the investigation of single gene disorders, its use is complementary to gene sequencing approaches that can detect point mutations but not dosage abnormalities.

3) Triplet repeat expansions

Pathological expansion of trinucleotide repeats within certain genes causes a range of neurological and neuromuscular diseases, known collectively as triplet repeat disorders. For many years Southern blotting was the predominant technique for investigating triplet repeat expansions, however PCR-based techniques have now largely superseded Southern blotting. You will be introduced to both Southern blotting and these PCR-based techniques.

What happens at each stage of PCR?

What happens at each stage of PCR?

Denaturing stage

  • During this stage the cocktail containing the template DNA and all the other core ingredients is heated to 94-95⁰C.
  • The high temperature causes the hydrogen bonds between the bases in two strands of template DNA to break and the two strands to separate.
  • This results in two single strands of DNA, which will act as templates for the production of the new strands of DNA.
  • It is important that the temperature is maintained at this stage for long enough to ensure that the DNA strands have separated completely.
  • This usually takes between 15-30 seconds.

Annealing stage

  • During this stage the reaction is cooled to 50-65⁰C. This enables the primers to attach to a specific location on the single-stranded template DNA by way of hydrogen bonding (the exact temperature depends on the melting temperature of the primers you are using).
  • Primers are single strands of DNA or RNA sequence that are around 20 to 30 bases in length.
  • The primers are designed to be complementary in sequence to short sections of DNA on each end of the sequence to be copied.
  • Primers serve as the starting point for DNA synthesis. The polymerase enzyme can only add DNA bases to a double strand of DNA. Only once the primer has bound can the polymerase enzyme attach and start making the new complementary strand of DNA from the loose DNA bases.
  • The two separated strands of DNA are complementary and run in opposite directions (from one end - the 5’ end – to the other - the 3’ end); as a result, there are two primers – a forward primer and a reverse primer.
  • This step usually takes about 10-30 seconds.

Extending stage

  • During this final step, the heat is increased to 72⁰C to enable the new DNA to be made by a special Taq DNA polymerase enzyme which adds DNA bases.
  • Taq DNA polymerase is an enzyme taken from the heat-loving bacteria Thermus aquaticus.
    • This bacteria normally lives in hot springs so can tolerate temperatures above 80⁰C.
    • The bacteria's DNA polymerase is very stable at high temperatures, which means it can withstand the temperatures needed to break the strands of DNA apart in the denaturing stage of PCR.
    • DNA polymerase from most other organisms would not be able to withstand these high temperatures, for example, human polymerase works ideally at 37˚C (body temperature).
  • 72⁰C is the optimum temperature for the Taq polymerase to build the complementary strand. It attaches to the primer and then adds DNA bases to the single strand one-by-one in the 5’ to 3’ direction.
  • The result is a brand new strand of DNA and a double-stranded molecule of DNA.
  • The duration of this step depends on the length of DNA sequence being amplified but usually takes around one minute to copy 1,000 DNA bases (1Kb).

  • These three processes of thermal cycling are repeated 20-40 times to produce lots of copies of the DNA sequence of interest.
  • The new fragments of DNA that are made during PCR also serve as templates to which the DNA polymerase enzyme can attach and start making DNA.
  • The result is a huge number of copies of the specific DNA segment produced in a relatively short period of time.  
Illustration showing how the polymerase chain reaction (PCR) produces lots of copies of DNA.
Illustration showing how the polymerase chain reaction (PCR) produces lots of copies of DNA. Image credit: Genome Research Limited

Source:-https://www.yourgenome.org/facts/what-is-pcr-polymerase-chain-reaction.

How does PCR work?

How does PCR work?

  • The principles behind every PCR, whatever the sample of DNA, are the same.
  • Five core ‘ingredients’ are required to set up a PCR. We will explain exactly what each of these do as we go along. These are:
    • the DNA template to be copied
    • primers, short stretches of DNA that initiate the PCR reaction, designed to bind to either side of the section of DNA you want to copy
    • DNA nucleotide bases (also known as dNTPs). DNA bases (A, C, G and T) are the building blocks of DNA and are needed to construct the new strand of DNA
    • Taq polymerase enzyme to add in the new DNA bases
    • buffer to ensure the right conditions for the reaction.
  • PCR involves a process of heating and cooling called thermal cycling which is carried out by machine.
  • There are three main stages:
    1. Denaturing – when the double-stranded template DNA is heated to separate it into two single strands.
    2. Annealing – when the temperature is lowered to enable the DNA primers to attach to the template DNA.
    3. Extending – when the temperature is raised and the new strand of DNA is made by the Taq polymerase enzyme.
  • These three stages are repeated 20-40 times, doubling the number of DNA copies each time.
  • A complete PCR reaction can be performed in a few hours, or even less than an hour with certain high-speed machines.
  • After PCR has been completed, a method called electrophoresis can be used to check the quantity and size of the DNA fragments produced.
Illustration showing the main steps in the polymerase chain reaction (PCR).
Illustration showing the main steps in the polymerase chain reaction (PCR). Image credit: Genome Research Limited

source:-https://www.yourgenome.org/facts/what-is-pcr-polymerase-chain-reaction

What is PCR (polymerase chain reaction)?

What is PCR?

  • The polymerase chain reaction (PCR) was originally developed in 1983 by the American biochemist Kary Mullis. He was awarded the Nobel Prize in Chemistry in 1993 for his pioneering work.
  • PCR is used in molecular biology to make many copies of (amplify) small sections of DNA or a gene.
  • Using PCR it is possible to generate thousands to millions of copies of a particular section of DNA from a very small amount of DNA.
  • PCR is a common tool used in medical and biological research labs. It is used in the early stages of processing DNA for sequencing, for detecting the presence or absence of a gene to help identify pathogens during infection, and when generating forensic DNA profiles from tiny samples of DNA.
  • Source:-https://www.yourgenome.org/facts/what-is-pcr-polymerase-chain-reaction

Wednesday, 6 June 2018


STARVATION

Starvation 


Prolonged fasting may result from an inability to obtain food, from the desire to lose weight rapidly, or in clinical situations in which an individual can not eat because of trauma,surgery, neoplasms, burns etc or even indepression (As in the given case) . In the absence of food the plasma levels of glucose, amino acids and triacylglycerols fall, triggering a decline in insulin secretion and an increase in glucagon release. The decreased insulin to glucagon ratio, and the decreased availability of circulating substrates, make this period of nutritional deprivation a catabolic state, characterized by degradation of glycogen, triacylglycerol and protein. This sets in to motion an exchange of substrates between liver,adipose tissue, muscle and brain that is guided by two priorities (i) the need to maintain glucose level to sustain the energy metabolism of brain ,red blood cells and other glucose requiring cells and (ii) to supply energy to other tissues by mobilizing fatty acids from adipose tissues and converting them to ketone bodies to supply energy to other cells of the body.


Fuel Stores
Atypical well­nourished70­kg man has fuel reserves totaling about 161,000 kcal (670,000 kJ).  The energy need for a 24­hour period ranges from about 1600 kcal (6700 kJ) to 6000 kcal (25,000 kJ), depending on the extent of activity. Thus, stored fuels suffice to meet caloric needs in starvation for 1 to 3 months. However, the carbohydrate reserves are exhausted in only a day. Energy supply during starvation During starvation the energy needs are  fulfilled by three types of fuels, glucose, fatty acids and ketone bodies. a) Glucose supply during starvation (Gluconeogenesis) 11/20/2016 Case Studies | Biochemistry for Medics – Lecture Notes http://www.namrata.co/category/diet­and­nutrition/case­studies­diet­and­nutrition/ 6/11 Energy needs of brain and RBCs Even under  conditions of starvation, the blood­glucose level has been maintained above 2.2 mM (40 mg/dl). The first priority of metabolism in starvation is to provide sufficient glucose to the brain and other tissues(such as red blood cells) that are absolutely dependent on this fuel.However, precursors of glucose are not abundant. Most energy is stored in the fatty acyl moieties of triacylglycerols. Fatty acids cannot be converted into glucose, because acetyl CoA cannot be transformed into pyruvate. The glycerol moiety of triacylglycerol can be converted into glucose, but only a limited amount is available. The only other potential source of glucose is amino acids derived from the breakdown of proteins. However, proteins are not stored,and so any breakdown will necessitate a loss of function. Thus, the second priority of metabolism in starvation is to preserve protein,which is accomplished by shifting the fuel being used from glucose to fatty acids and ketone bodies by cells  other than brain cells and the cells lacking mitochondria. It is a biological compromise to provide glucose to these cells as a priority. During prolonged starvation , when the gluconeogenic precursors are not available, proteins are however  broken down to use carbon skeleton of  glucogenic amino acids for glucose production. b) Fatty acid oxidation Energy need of liver The low blood­sugar level leads to decreased secretion of insulin and increased secretion of glucagon. Glucagon stimulates the mobilization of triacylglycerols in adipose tissue and gluconeogenesis in the liver. The liver obtains energy for its own needs by oxidizing fatty acids released from adipose tissue. The concentrations of acetyl Co A and citrate consequently increase, which switch off glycolysis. Thus glucose utilization is stopped in liver cells to preserve glucose for priority cells Energy need of muscles The uptake of glucose by muscle is markedly diminished because of the low insulin level, whereas fatty acids enter freely.Consequently, muscle shifts almost entirely from glucose to fatty acids for fuel.The beta­oxidation of fatty acids by muscle halts the conversion of pyruvate into acetyl CoA, because acetyl CoA stimulates the phosphorylation of the pyruvate dehydrogenase complex, which renders it inactive. Most of the pyruvate is transaminated to alanine, at the expense of amino acids arising from breakdown of “labile” protein reserves synthesized in the fed state. The alanine, lactate and much of the keto­acids resulting from this transamination are exported from muscle, and taken up by the liver, where the alanine is transaminated to yield pyruvate. Pyruvate is a major substrate for gluconeogenesis in the liver.(Figure­1) 11/20/2016 Case Studies | Biochemistry for Medics – Lecture Notes http://www.namrata.co/category/diet­and­nutrition/case­studies­diet­and­nutrition/ 7/11 Figure- 1-showing Glucose Alanine and Cori’s cycle In adipose tissue the decrease in insulin and increase in glucagon results in activation of intracellular hormonesensitive lipase.This leads to release from adipose tissue of increased amounts of glycerol(which is a substrate for gluconeogenesis in the liver) and free fatty acids,which are used by liver, heart, and skeletal muscle as their preferred metabolic fuel, therefore sparing glucose. Loss of muscle mass During starvation, degraded proteins are not replenished and serve as carbon sources for glucose synthesis. Initial sources of protein are those that turn over rapidly, such as proteins of the intestinal epithelium and the secretions of the pancreas. Proteolysis of muscle protein provides some of three­carbon precursors of glucose. The nitrogen part of the amino acids is converted to urea (BUN) c) Ketosis Energy need of peripheral tissues After about 3 days of starvation, the liver forms large amounts of acetoacetate and beta­ hydroxybutyrate. Their synthesis from acetyl CoA increases markedly because the citric acid cycle is unable to oxidize all the acetyl units generated by the degradation of fatty acids. Gluconeogenesis depletes the supply of oxaloacetate, which is essential for the entry of acetyl CoA into the citric acid cycle. (Figure­2) Consequently, the liver produces large quantities of ketone bodies, which are released into the blood. At this time, the brain begins to consume appreciable amounts of acetoacetate in place of glucose. After 3 days of starvation, about a third of the energy needs of the brain are met by ketone bodies. The heart also uses ketone bodies as fuel. After several weeks of starvation, ketone bodies become the major fuel of the brain. 11/20/2016 Case Studies | Biochemistry for Medics – Lecture Notes http://www.namrata.co/category/diet­and­nutrition/case­studies­diet­and­nutrition/ 8/11 Figure­ 2­fatty acid oxidation and ketosis during starvation. In essence, ketone bodies are equivalents of fatty acids that can pass through the blood­brain barrier. Only 40 g of glucose is then needed per day for the brain, compared with about 120 g in the first day of starvation. The effective conversion of fatty acids into ketone bodies by the liver and their use by the brain markedly diminishes the need for glucose. Hence, less muscle is degraded than in the first days of starvation. The breakdown of 20 g of muscle daily compared with 75 g early in starvation is most important for survival. A person’s survival time is mainly determined by the size of the triacylglycerol depot. What happens after depletion of the triacylglycerol stores? The only source of fuel that remains is proteins. Protein degradation accelerates, and death inevitably results from a loss of heart, liver, or kidney function. 

Wednesday, 9 November 2016

ENDOCRINOLOGY CASES

Case- 1

A 30 yr old woman, fractured her skull in an accident. She had no major injuries, no significant blood loss and her cardiovascular system was stable. She was unconscious for 2 days after the accident. On the 4th day of her admission to hospital, she was noted to be producing large volumes of urine and complaining of thirst.
Biochemical findings were:
Na+        K+      Cl-       HCO3-    Urea                           Creatinine       Glucose
150       3.6     106      25           5.5    mmol/L            80 μmol/L          5.4 mmol/L
Serum osmolality  = 310 mmol/kg
Urine osmolality = 110 mmol/kg

Urine volume = 8L/ day


Solution:-

One can make a confident diagnosis of central diabetes insipidus from the history of head trauma and the observation that she was producing large volumes of urine and complaining of thirst. Her blood glucose level excludes diabetes mellitus as a cause of her polyuria and her hypernatraemia accounts for her thirst. In normal circumstances a serum sodium concentration of 150 mmol/L will stimulate AVP production and cause the urine to be maximally concentrated. This patient’s urinemis, therefore, inappropriately dilute. It would be unnecessary and even dangerous to attempt to perform a water deprivation test on this patient. Note that her serum urea is not increased. This reflects her high urine flow-rate despite her significant water depletion.

Cases 2

A 31 year old woman was admitted to a surgical ward with a  2 day history of abdominal pain and vomiting. Her BP was 110/65 mmHg and her pulse 88 beats per minute and regular. A provisional diagnosis of intestinal obstruction was made.
On admission, tests showed:
Na+    K+      Cl-         HCO3-     Urea                      Creatinine
128     6.1    92         18           10.8  mmol/L           180μmol/L
She was given 1.5 L of 0.9% saline intravenously, overnight and the following morning her symptoms had resolved. Her serum sodium had increased to 134mmol/L and her serum potassium had fallen to 4.8 mmol/L. On reviewing her history, she had been unwell for a number of months with weight loss and anorexia. She had noted to be pigmented. Her cortisol levels were less than 60nmol/L

Solution:-

This presentation is classical of acute adrenal failure with characteristic symptoms, physical findings and electrolyte pattern. The diagnosis is confirmed by the Synacthen test. On presentation, this woman was sodium depleted with pre-renal uraemia. As her ECF was expanded with 0.9%
sodium chloride, this improved her glomerular filtration rate, which is sufficient, even in the absence of aldosterone, to correct the hyperkalaemia by increasing her urinary potassium excretion. The reduction in this patient’s blood volume will stimulate vasopressin secretion, giving rise to the hyponatraemia. The sodium chloride infusion by restoring her blood volume will inhibit AVP secretion, enabling her to correct the hyponatraemia.

Rare Diseaes Some examples of rare diseases are  Spinal Muscular Atrophy ,   Osteogenesis imperfecta ,   Achondroplasia   or   Rett Syndrome...